CAR T-Cell Therapy For Autoimmune Disease: What We Know Now
Originally published November 17, 2023 | Updated September 29, 2026
What CAR T-Cell Therapy Means for the Future of Autoimmune Disease Treatment
Chimeric antigen receptor (CAR) T-cell therapy, a form of cellular immunotherapy first developed to treat certain blood cancers, is now being investigated as a potential treatment for severe autoimmune diseases.
Much of the research has focused on using CAR T cells to deeply deplete B cells, including abnormal B-cell populations that contribute to autoantibody production and autoimmune disease. The goal is ambitious: rather than continuously suppressing the immune system with medication, researchers are investigating whether a one-time treatment could effectively “reset” parts of the immune system and produce long-lasting remission.
Early studies in people with severe, treatment-resistant systemic lupus erythematosus, systemic sclerosis (scleroderma), inflammatory myositis, and other autoimmune diseases have reported substantial improvements, in some cases lasting after B cells returned and immunosuppressive medications were discontinued. Research has since expanded to additional diseases and new approaches designed to make CAR T-cell therapy more effective, accessible, and potentially safer.
However, CAR T-cell therapy remains experimental for autoimmune disease.
Important questions remain about who may benefit, how long responses last, and how to reduce the risks and complexity of treatment. Serious adverse events reported in several clinical trials in 2026 have also underscored the need to better understand the safety of these powerful therapies as studies expand to larger numbers of people.
You may be wondering,
What is CAR T-Cell Therapy?
How Could CAR T-Cell Therapy Treat Autoimmune Disease?
Can CAR T-Cell Therapy “Reset” the Immune System?
What Has More Recent CAR T-Cell Research Shown?
How Is CAR T-Cell Therapy Evolving?
What Are the Risks of CAR T-Cell Therapy?
What Could CAR T-Cell Therapy Mean for the Future of Autoimmune Disease Treatment?
What Is CAR T-Cell Therapy?
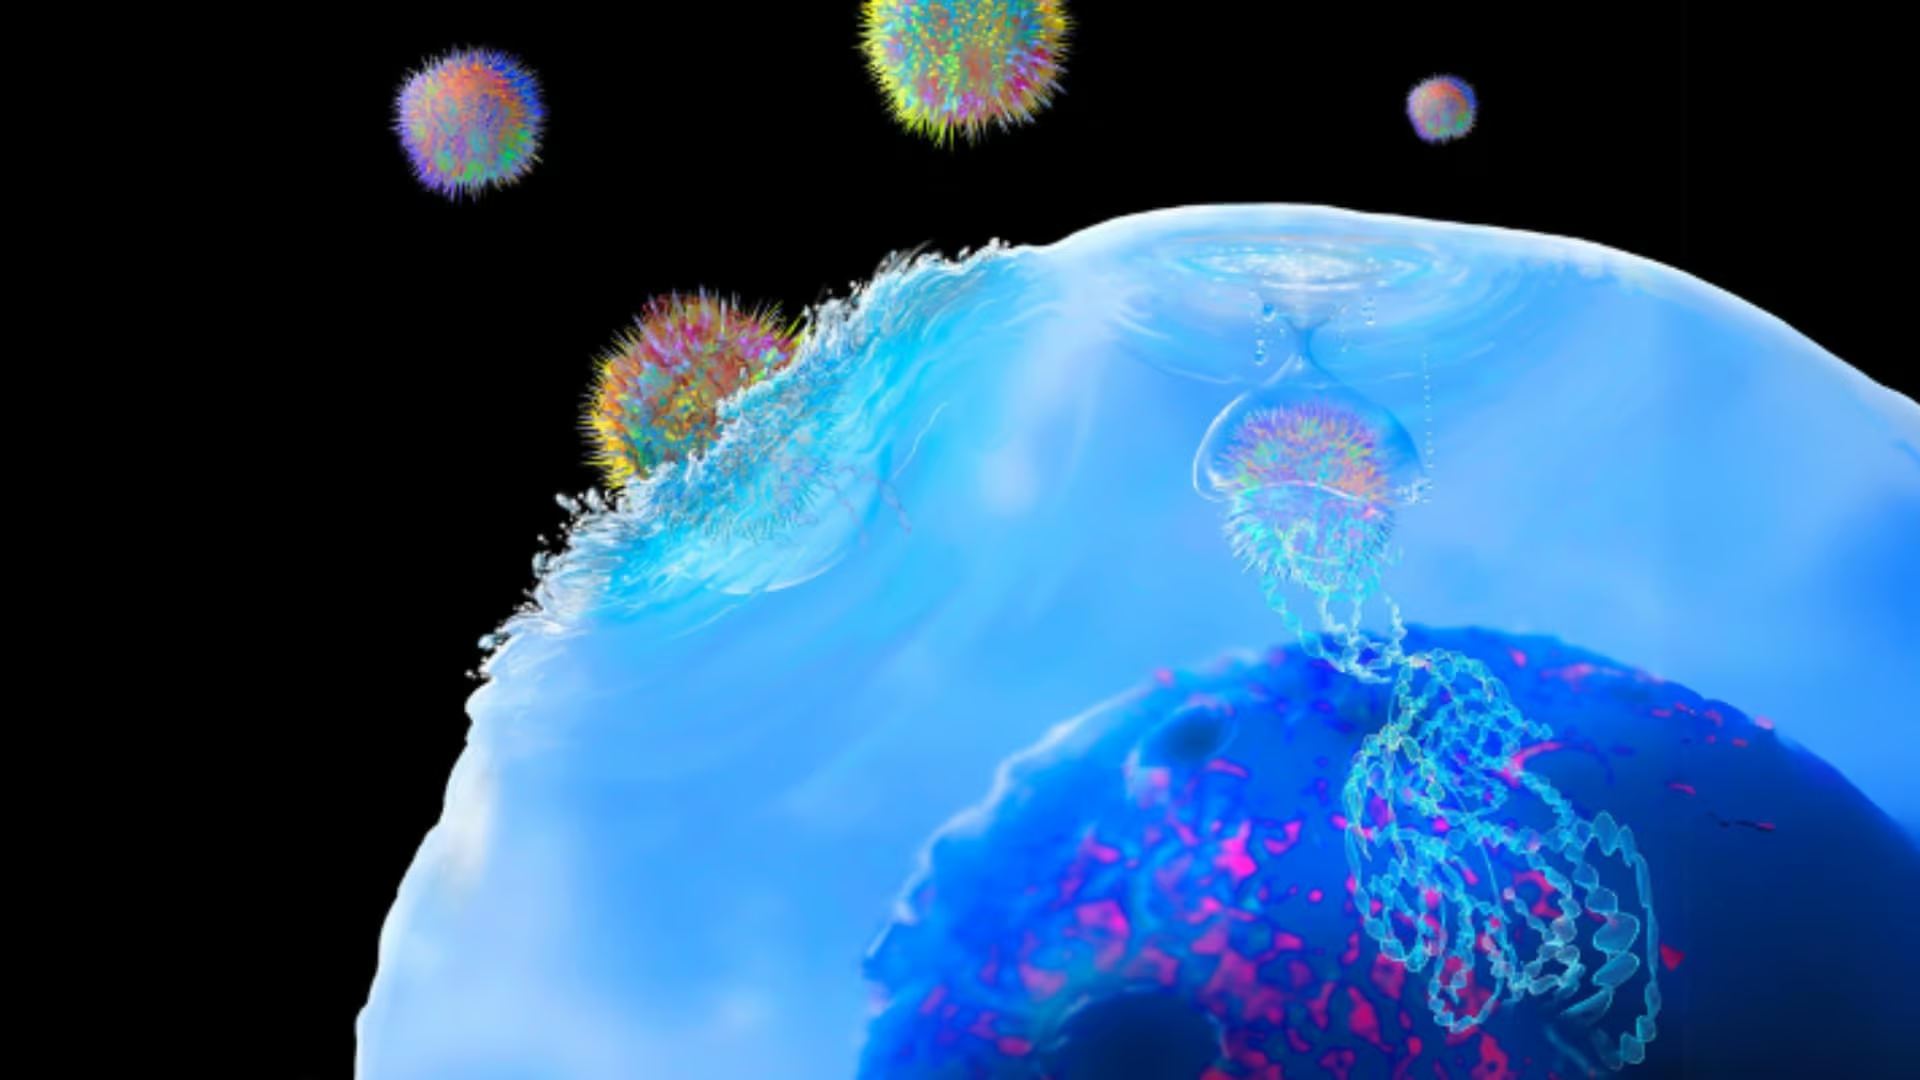
CAR T-cell therapy uses genetically modified T cells, a type of immune cell, to recognize and attack cells carrying a specific target.
The process generally involves several steps:
- Collection of T cells: T cells are extracted from the patient’s blood through a process called leukapheresis.
- Genetic modification: In the laboratory, these T cells are genetically engineered to express a synthetic receptor called a chimeric antigen receptor (CAR). This receptor is designed to recognize specific proteins on the surface of target cells.
- Expansion: The modified T cells are then multiplied to create a large number of CAR-T cells.
- Preconditioning: With many CAR T-cell therapies, a short course of chemotherapy called lymphodepletion is given before the CAR T cells are infused. This reduces existing immune cells and creates an environment that helps the engineered cells expand.
- Infusion and targeting: The CAR T cells are infused back into the bloodstream, where they can recognize cells carrying their target, become activated, and destroy them.
Unlike a conventional medication, CAR T cells are living immune cells. Once infused, they can expand within the body and continue functioning after the initial treatment.
CAR T-cell therapies are already approved by the U.S. Food and Drug Administration (FDA) for several blood cancers, but no CAR T-cell therapy is currently FDA-approved to treat autoimmune disease.
How Could CAR T-Cell Therapy Treat Autoimmune Disease?
Most autoimmune CAR T-cell research has focused on B cells, immune cells that normally help protect the body from infection by producing antibodies and performing other immune functions.
In several autoimmune diseases, abnormal B cells contribute to disease by producing autoantibodies, activating other immune cells, and sustaining inflammation. Treatments that reduce B cells are already used for some autoimmune diseases.
Many experimental autoimmune CAR T-cell therapies target CD19, a protein expressed across much of the B-cell lineage. Once engineered to recognize CD19, CAR T cells can seek out and destroy CD19-positive B cells.
Researchers are interested in whether CAR T cells can produce a deeper form of B-cell depletion than existing therapies. Disease-associated B cells do not exist only in the bloodstream. Some can persist in tissues, lymph nodes, and other areas that may be more difficult for conventional therapies to reach.
This possibility is also being investigated in multiple sclerosis (MS). Researchers at Yale School of Medicine are studying whether CD19-targeted CAR T cells can reach disease-associated B cells beyond the bloodstream, including within the central nervous system.
The goal is not simply to suppress immune activity temporarily. Researchers hope that removing a broad population of B cells involved in autoimmunity may allow a healthier B-cell population to emerge as the immune system rebuilds.
Can CAR T-Cell Therapy “Reset” the Immune System?
The idea of an immune “reset” is one of the most intriguing aspects of CAR T-cell therapy for autoimmune disease.
After CD19 CAR T-cell treatment, B cells can eventually return. But early studies suggest that the returning B-cell population may differ from the one present before treatment.
A landmark study published in The New England Journal of Medicine in 2024 followed 15 people with severe autoimmune disease who received CD19 CAR T-cell therapy: eight with systemic lupus erythematosus (SLE), three with idiopathic inflammatory myositis, and four with systemic sclerosis.
All eight participants with lupus achieved remission according to established criteria. All three participants with inflammatory myositis achieved a major clinical response, while all four with systemic sclerosis experienced decreased disease activity. All 15 were able to discontinue immunosuppressive therapy during the reported follow-up period, which ranged from four to 29 months.
B cells eventually returned, but clinical improvement persisted in many participants. Researchers observed the reappearance of predominantly naïve B cells rather than simply the return of the previous B-cell population.
These findings helped support the idea that CAR T-cell therapy might interrupt an established autoimmune response and allow parts of the immune system to rebuild differently.
However, “immune reset” remains a working concept rather than a guarantee. Researchers still need longer follow-up and larger studies to determine how often remission persists, why some people may relapse, and whether the rebuilt immune system remains different over many years.
What Has More Recent CAR T-Cell Research Shown?
Since the earliest case reports, CAR T-cell research in autoimmune disease has begun moving into larger and more structured clinical trials.
Published in Nature Medicine in January 2026, the Phase 1/2a CASTLE trial evaluated CD19 CAR T-cell therapy in people with treatment-resistant SLE, systemic sclerosis, and idiopathic inflammatory myopathies. The basket-trial design allowed researchers to study the same treatment across multiple B-cell-mediated autoimmune diseases, reflecting the possibility that different autoimmune conditions may share immune mechanisms that can be targeted by the same cellular therapy.
Industry-sponsored programs are also expanding.
Cabaletta Bio is studying its investigational CD19 CAR T-cell therapy, resecabtagene autoleucel (rese-cel), across several autoimmune diseases. At the 2026 European Alliance of Associations for Rheumatology (EULAR) Congress, the company reported interim results from 52 evaluable participants with lupus, myositis, or systemic sclerosis. Among participants with dermatomyositis, five of six achieved a moderate-to-major improvement response at 16 weeks while off immunomodulatory treatment, and those responses were maintained through the latest reported follow-up, extending as long as 1.5 years. Improvements were also reported among participants with systemic sclerosis. These are interim company-reported findings from ongoing studies rather than results from completed randomized trials.
Clinical research has expanded beyond rheumatic diseases as well. CAR T-cell approaches are now being investigated in neurological and antibody-mediated autoimmune diseases, including MS, myasthenia gravis, and pemphigus vulgaris.
How Is CAR T-Cell Therapy Evolving?
Traditional CAR T-cell therapy is highly personalized. A person’s own T cells must be collected, genetically modified, expanded, tested, and returned to that individual. Researchers are now investigating ways to make this process more effective and accessible.
One approach is to target more than one immune cell population. CD19 CAR T cells target B cells, but some long-lived plasma cells that produce autoantibodies may lack CD19.
In a 2025 Phase 1 trial involving 15 people with treatment-resistant lupus, researchers combined CAR T cells targeting CD19 with CAR T cells targeting B-cell maturation antigen (BCMA), which is expressed by plasma cells. Twelve of the 15 participants met both low-disease-activity and remission criteria by 12 weeks. Researchers also observed elimination of autoreactive cell populations and reconstitution of predominantly naïve B cells.
Another strategy involves allogeneic, or donor-derived, cell therapy. Instead of creating a new treatment from each person’s own cells, researchers are investigating engineered donor cells that could potentially be prepared in advance. A small Phase 1 study published in 2025 evaluated one such approach in five people with severe, treatment-resistant lupus and lupus nephritis.
Researchers are even investigating whether CAR T cells can be created inside the body.
In 2025, researchers reported an early in vivo approach that used lipid nanoparticles to deliver genetic instructions to T cells inside people with treatment-resistant lupus. The treatment generated CD19 CAR T cells without first removing and engineering the cells in a laboratory. Researchers reported B-cell depletion and reduced disease activity in this small early study.
These approaches remain experimental, but they illustrate how rapidly CAR T-cell technology is evolving beyond the original model developed for cancer.
Another Approach: T-Cell Engagers
CAR T-cell therapy is not the only strategy researchers are using to harness T cells against disease-associated B cells. Clinical trials are also investigating T-cell engagers (TCEs), including bispecific antibodies designed to bind a target on B cells and CD3 on T cells at the same time. This brings the two cells together and directs the person’s existing T cells to attack the targeted B cells.
Unlike traditional CAR T-cell therapy, T-cell engagers do not require T cells to be removed from the body, genetically engineered, expanded in a laboratory, and reinfused. Researchers are now studying T-cell engagers in autoimmune diseases including lupus, rheumatoid arthritis, systemic sclerosis, Sjögren disease, and inflammatory myopathies.
Whether these treatments can achieve the same depth and durability of B-cell depletion being investigated with CAR T-cell therapy remains an important question.
What Are the Risks of CAR T-Cell Therapy?
CAR T-cell therapy can produce powerful immune effects, which also creates important risks.
One of the best-known complications is cytokine release syndrome (CRS), an inflammatory response caused by rapid immune activation. Symptoms can include fever, fatigue, low blood pressure, difficulty breathing, and, in severe cases, organ dysfunction.
Another potential complication is immune effector cell-associated neurotoxicity syndrome (ICANS), which can cause confusion and other neurological symptoms.
CAR T-cell treatment and the lymphodepleting chemotherapy often given beforehand can also temporarily reduce normal immune cells and blood counts, increasing vulnerability to infection and other complications.
The early autoimmune disease studies initially produced encouraging safety results. In the 15-person 2024 case series, CRS was mostly mild, with one case of grade 2 CRS. One participant experienced grade 1 ICANS.
However, serious safety concerns emerged as autoimmune CAR T-cell trials expanded.
In August 2026, Novartis paused eight clinical trials of its investigational CAR T-cell therapy rapcabtagene autoleucel (rap-cel) in autoimmune and neurological diseases after three participants died following a severe immune reaction. The affected research program included diseases such as lupus, rheumatoid arthritis, vasculitis, MS, and myasthenia gravis. Novartis reported that it was investigating the events with independent safety boards and health authorities.
Bristol Myers Squibb also voluntarily paused studies of its investigational CD19 CAR T-cell therapy zola-cel while reviewing safety data after participants experienced inflammatory reactions that the company described as temporary and reversible.
These developments do not erase the encouraging results reported in other CAR T-cell programs, but they reinforce why larger trials and careful long-term monitoring are essential before the overall benefits and risks of CAR T-cell therapy for autoimmune disease can be understood.
Safety is not the only obstacle.
Traditional CAR T-cell therapy requires specialized facilities and a complex manufacturing process. The time required to collect and engineer cells can also make treatment difficult to scale.
Most autoimmune CAR T-cell protocols have additionally required lymphodepleting chemotherapy before infusion. Researchers are investigating whether this step can be reduced or eliminated. In 2026, Cabaletta Bio began reporting early results from participants receiving rese-cel without traditional preconditioning, although this approach remains in early clinical testing.
Cost is another important question. Existing commercial CAR T-cell therapies for cancer are expensive and require substantial healthcare resources. Because there is currently no approved CAR T-cell treatment for autoimmune disease, however, there is no established price for autoimmune CAR T-cell therapy.
Researchers will ultimately need to determine not only whether CAR T-cell therapies can produce lasting remission, but whether they can be delivered safely and practically to a broader population.
What Could CAR T-Cell Therapy Mean for the Future of Autoimmune Disease Treatment?
CAR T-cell therapy represents a fundamentally different way of thinking about autoimmune disease treatment.
Many existing treatments are designed to control inflammation or suppress parts of the immune response over time. CAR T-cell therapy raises the possibility that, for some people with severe autoimmune disease, a short course of treatment could instead eliminate disease-associated immune cells deeply enough to produce prolonged remission without continuous immunosuppression.
Early clinical results provide evidence that this may be possible in at least some people. At the same time, the number of people treated remains relatively small, follow-up is limited compared with the lifelong course of many autoimmune diseases, and recent serious safety events demonstrate how much remains to be understood.
Researchers are now trying to determine which autoimmune diseases are most responsive to CAR T-cell therapy, which immune cells should be targeted, which people are most likely to benefit, how durable responses are, and whether newer approaches can make treatment safer and more accessible.
For now, CAR T-cell therapy remains an experimental treatment for autoimmune disease.
But research has advanced considerably from the first lupus case reports. What began as an unexpected extension of a cancer treatment has become a rapidly developing area of autoimmune disease research, one that is testing whether the immune system can be not only suppressed, but potentially rebuilt in a healthier state.

Sources
- Article Sources
American College of Rheumatology. (2023 November 7). CAR-T Cell Therapy Leads to Long-Term Remission in Lupus while Maintaining Vaccine Response. https://rheumatology.org/press-releases/car-t-cell-therapy-leads-to-long-term-remission-in-lupus-while-maintaining-vaccine-response
Dai, X., Park, J. J., Du, Y., Kim, H. R., Wang, G., Errami, Y., & Chen, S. (2019). One-step generation of modular CAR-T cells with AAV-Cpf1. Nature methods, 16(3), 247–254. https://doi.org/10.1038/s41592-019-0329-7
Isaacs J. D. (2024). CAR T Cells – A New Horizon for Autoimmunity?. The New England journal of medicine, 390(8), 758–759. https://doi.org/10.1056/NEJMe2400203
Feng, J., Huo, D., Hong, R., Jin, X., Cao, H., Shao, M., Wen, R., Zhang, Q., Zhang, M., Fu, S., Wang, D., Xu, H., Wei, G., Cui, J., Huang, S., Cui, D., Chang, A. H., Liu, Z., Lu, L., Lin, J., … Huang, H. (2025). Co-infusion of CD19-targeting and BCMA-targeting CAR-T cells for treatment-refractory systemic lupus erythematosus: a phase 1 trial. Nature medicine, 31(11), 3725–3736. https://doi.org/10.1038/s41591-025-03937-8
Wang, X., Zhang, Y., Wang, H., Wu, X., He, C., Lin, S., Pang, K., Li, Y., Chen, Y., Tang, X., Liu, X., Wang, J., Ye, S., Yan, R., Guan, T., Dai, B., Lu, J., He, H., Lin, L., Lu, H., … Xu, H. (2025). Allogeneic CD19-targeting T cells for treatment-refractory systemic lupus erythematosus: a phase 1 trial. Nature medicine, 31(11), 3713–3724. https://doi.org/10.1038/s41591-025-03899-x
Wang, Q., Xiao, Z. X., Zheng, X., Wang, G., Yang, L., Shi, L., Xiang, N., Wang, X., Zha, G. F., Schett, G., & Chen, Z. (2025). In Vivo CD19 CAR T-Cell Therapy for Refractory Systemic Lupus Erythematosus. The New England journal of medicine, 393(15), 1542–1544. https://doi.org/10.1056/NEJMc2509522
Müller, F., Hagen, M., Wirsching, A., Kharboutli, S., Aigner, M., Völkl, S., Kretschmann, S., Tascilar, K., Taubmann, J., Bucci, L., Raimondo, M. G., Bergmann, C., Rothe, T., Corte, G., Tur, C., Muñoz, L., Böltz, S., Schuster, L., Hartmann, F., Garantziotis, P., … Schett, G. (2026). CD19 CAR-T cells for treatment-refractory autoimmune diseases: the phase 1/2 CASTLE basket trial. Nature medicine, 32(3), 1142–1151. https://doi.org/10.1038/s41591-025-04185-6
Cabaletta Bio. Cabaletta Bio Announces New Rese-cel Data and Development Updates Across Autoimmune Portfolio. June 3, 2026.
Reuters. Novartis pauses trials of experimental cell therapy after three deaths. September 1, 2026.
MacMillan C. Enhancing CAR-T Therapy: From Cancer to Autoimmune Diseases. Yale School of Medicine. September 29, 2026.